Labiaplasty for Physical Discomfort: Pinching, Appearance, and Clitoromegaly
A 30-year-old mother of two had a labiaplasty and hood reduction with the added complexity of clitoromegaly — an enlarged clitoris requiring careful balancing of the hood and labia to achieve a natural, proportional result.
Case Story
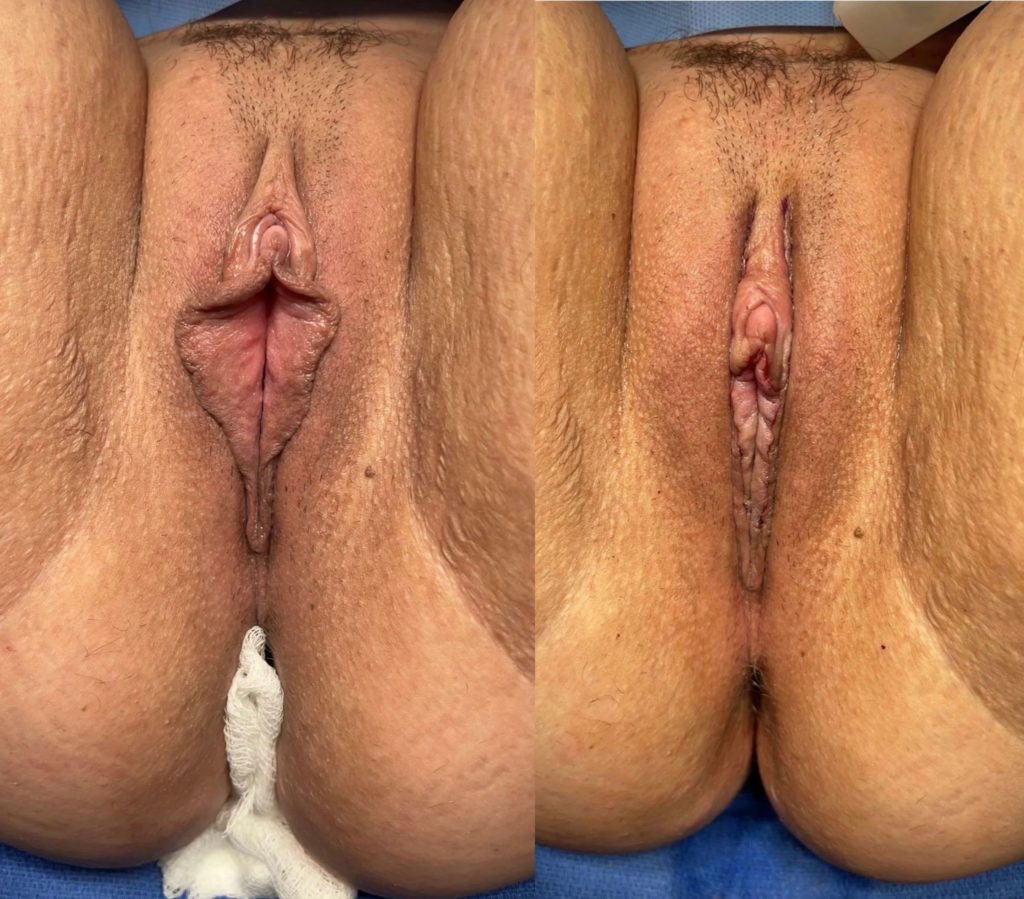
Today I had the honor of performing a labiaplasty and hood reduction on a 30-year-old mother of two. She was unhappy with the appearance of her vagina and also experienced physical symptoms: pinching of the labia with clothing, exercise, and sexual intercourse. She came in with clear goals and a clear understanding of what she wanted.
She also presented with clitoromegaly — an enlargement of the clitoris — which can develop from elevated androgen levels. It can be irreversible over time: once the clitoris becomes gradually enlarged, it often does not reduce in size on its own. This finding is sometimes seen in patients who have used testosterone in the past, or in women who naturally produce higher levels of androgen hormones.
The key in this case was balancing the hood reduction and labia minora reduction with the slightly enlarged and protuberant clitoris. We needed to leave ample hood tissue for coverage while still reducing the hood sufficiently to create balance. She was awake with oral sedation (Valium) and could follow along. I am very happy with how the case turned out — the hood is reduced, the labia minora are reduced, and the clitoris retains appropriate coverage.
Post-procedure result
Procedure Highlights
Labia minora reduction
Clitoral hood reduction balanced with clitoromegaly
Ample hood tissue preserved for clitoral coverage
Addressed pinching with clothing, exercise, and intercourse
Oral sedation (Valium) for comfort
Clitoromegaly from androgen levels — carefully accommodated in surgical plan
Surgical Philosophy and Teaching Points
What Is Clitoromegaly?
Clitoromegaly refers to enlargement of the clitoris beyond typical size. It can develop from elevated androgen (testosterone) levels — naturally occurring or from exogenous use — and is often irreversible. It does not typically affect function, but it changes the anatomy of the vulva and must be factored into any labiaplasty surgical plan that involves the clitoral hood.
Balancing Hood Reduction with an Enlarged Clitoris
When the clitoris is enlarged, the hood reduction must be conservative enough to preserve adequate coverage while still reducing excess hood tissue. Removing too much hood tissue when clitoromegaly is present would leave the clitoris exposed — which is not desirable aesthetically or functionally. The balance requires careful intraoperative judgment.
Physical Discomfort Drives Many Labiaplasty Decisions
Many women pursue labiaplasty for a combination of physical and aesthetic reasons. Pinching with clothing, discomfort during intercourse, and exercise-related irritation are all common functional complaints that a labiaplasty directly addresses. When both comfort and appearance are the motivation, patients tend to experience the highest levels of satisfaction with their results.
Frequently Asked Questions
What is clitoromegaly and can it be treated?
Clitoromegaly is an enlargement of the clitoris, often related to elevated androgen levels. It is typically irreversible. Dr. Oppenheimer does not surgically reduce the clitoris itself but adapts his hood reduction technique to work with the enlarged anatomy and maintain appropriate coverage.
Can labiaplasty be performed when clitoromegaly is present?
Yes. Clitoromegaly changes the surgical planning — specifically how much hood tissue is left for coverage — but it does not prevent a labiaplasty from being performed. The procedure is adapted to the anatomy.
Does labiaplasty relieve pinching during intercourse?
Yes. Excess labia minora tissue can be caught or compressed during intercourse, causing pain or discomfort. Reducing the labia minora eliminates this source of friction and improves comfort during sexual activity for most patients.
What is oral sedation for labiaplasty?
Oral sedation typically involves taking a benzodiazepine (such as Valium) before the procedure to reduce anxiety and promote relaxation. It works alongside local anesthesia, allowing the patient to remain awake but calm and comfortable throughout the surgery.
Can androgens cause the clitoris to enlarge?
Yes. Elevated androgen levels — whether from natural hormone variation, testosterone supplementation, or other androgen-containing medications — can cause clitoral enlargement over time. Once enlarged, the change is typically permanent.